Overview
Mumps is an acute viral infection caused by the
mumps virus, a member of the
Paramyxoviridae family. The disease spreads easily through respiratory droplets, saliva, or direct contact with contaminated surfaces, making it especially common in close‑living settings such as schools, colleges, and households. After an incubation period of about
16 to 18 days, most infected individuals develop nonspecific prodromal symptoms—low‑grade
fever,
headache,
malaise,
muscle aches, and
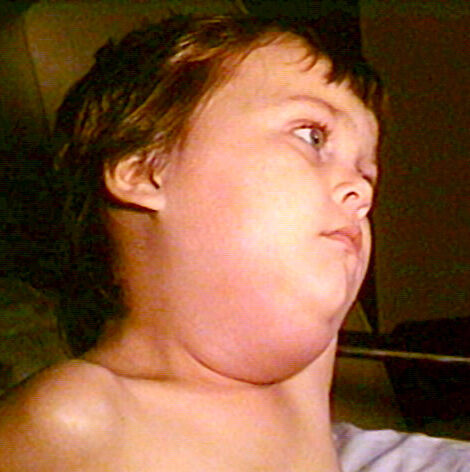
loss of appetite. Within a day or two, the hallmark sign appears: painful swelling of the
parotid glands located just in front of and below the ears, giving the classic “chipmunk cheeks” appearance.
Approximately one‑third of those infected remain asymptomatic, yet they can still transmit the virus to others. When symptoms do manifest, they usually resolve within 7–10 days, but complications such as orchitis (testicular inflammation), mastitis, meningitis, or pancreatitis can occur, particularly in adolescents and adults. Prompt medical evaluation is advised if swelling is severe, persists beyond a week, or is accompanied by high fever, severe headache, or neurological signs—these may signal complications that require professional care.
History/Background
Mumps has been recognized for centuries, with descriptions of “epidemic parotitis” appearing in medieval medical texts. The causative agent, the
mumps virus, was isolated in 1934 by Dr. Thomas Rivers and colleagues, confirming its viral nature. The first effective vaccine—a live‑attenuated strain derived from the Jeryl‑Lynn isolate—was licensed in the United States in 1967. Widespread adoption of the
MMR (measles‑mumps‑rubella) vaccine in the 1970s dramatically reduced global incidence. However, periodic outbreaks still occur, often linked to waning immunity, vaccine hesitancy, or densely populated settings. Notable resurgence events include the 2006 U.S. college outbreak and the 2015–2016 European surge, prompting renewed emphasis on booster doses for adolescents.
Key Information
-
Causative agent: Mumps virus, an enveloped, single‑stranded RNA virus.
-
Transmission: Respiratory droplets, saliva, direct contact; contagious from several days before symptom onset until the glands have fully resolved.
-
Incubation period: 12–25 days, most commonly 16–18 days.
-
Clinical presentation: Early nonspecific symptoms → painful
parotid swelling; may involve other salivary glands, testes, ovaries, pancreas, or central nervous system.
-
Asymptomatic rate: ~33 % of infections lack overt signs but remain infectious.
-
Complications: Orchitis (≈30 % of post‑pubertal males),
meningitis,
hepatitis,
pancreatitis,
hearing loss, and, rarely,
encephalitis.
-
Prevention: Two‑dose
MMR vaccine schedule (first dose at 12–15 months, second at 4–6 years); a third booster is recommended for high‑risk groups (college students, military personnel).
-
Management: No specific antiviral; treatment is supportive—rest, hydration, analgesics/antipyretics, and cold compresses for glandular pain. Isolation for at least five days after onset of parotitis helps curb spread.
-
When to seek care: Persistent high fever, severe facial swelling, sudden hearing changes, testicular pain, stiff neck, or signs of meningitis warrant immediate medical attention.
Significance
Mumps remains a public‑health benchmark for the success and challenges of vaccination programs. The disease’s dramatic visual hallmark makes it a useful teaching tool for viral pathogenesis and herd immunity concepts. Despite the availability of a safe, effective vaccine, periodic outbreaks highlight gaps in coverage, waning immunity, and the impact of misinformation. Understanding mumps also informs broader infectious‑disease strategies, such as the importance of booster doses and surveillance in congregate settings. Reducing mumps incidence prevents not only the discomfort of parotid swelling but also serious sequelae like infertility from orchitis and permanent hearing loss, underscoring the value of maintaining high vaccination rates worldwide.